
COVID-19 PHOSP-COVID Study

Regular Off Off

The PHOSP-COVID study aims to identify whether there are longer-term health problems of COVID-19 for those who were admitted to hospital.

The study aims to understand:

  • Why some people experience more severe COVID-19 than others
  • Why some people recover more quickly than others
  • Why some patients develop other health problems later on
  • Which treatments or interventions patients received in hospital or afterwards were helpful
  • How we can improve the care of patients after they have been discharged from hospital

Patients on the study will be assessed using techniques such as advanced imaging, data collection and analysis of blood and lung samples, creating a comprehensive picture of the impact COVID-19 has had on longer term health outcomes across the UK.

The PHOSP-COVID team will then develop trials of new strategies for clinical care, including personalised treatments for groups of patients based on the particular disease characteristics they show as a result of having COVID-19 to improve their long-term health.

This study is now closed. You can view the results below:


Study Results:

Study reveals seven in ten patients hospitalised with COVID-19 not fully recovered five months post-discharge

Key study findings:

  • Majority of patients hospitalised with COVID-19 have not fully recovered after 5 months
  • Those who experience more persistent symptoms tend to be middle-aged, white, female, with at least two ‘co-morbidities’, such as diabetes, lung or heart disease
  • Cognitive impairment, also referred to as ‘brain fog’, occurs as a predominant symptom in a sub-set of patients who tend to be older and male
  • A biological marker associated with inflammation, C-Reactive Protein (CRP), is elevated in all but the most mild of post-hospital cases

The majority of survivors who left hospital following COVID-19 did not fully recover five months after discharge and continued to experience negative impacts on their physical and mental health, as well as ability to work, according to results released by the PHOSP-COVID study today. Furthermore, one in five of the participant population reached the threshold for a new disability.

The UK-wide study, which is led by the National Institute for Health Research (NIHR) Leicester Biomedical Research Centre – a partnership between Leicester’s Hospitals, the University of Leicester and Loughborough University - and jointly funded by the NIHR and UK Research and Innovation, analysed 1077 patients who were discharged from hospital between March and November 2020 following an episode of COVID-19.

Researchers found that each participant had an average of nine persistent symptoms. The ten most common symptoms reported were: muscle pain, fatigue, physical slowing down, impaired sleep quality, joint pain or swelling, limb weakness, breathlessness, pain, short-term memory loss, and slowed thinking.

Patients were also assessed for mental health. The study reports that over 25 per cent of participants had clinically significant symptoms of anxiety and depression and 12 per cent had symptoms of post-traumatic stress disorder (PTSD) at their 5-month follow-up.

Of the 67.5 per cent of participants who were working before COVID, 17.8 per cent were no longer working, and nearly 20 per cent experienced a health-related change in their occupational status.

Professor Chris Brightling, a professor of respiratory medicine at the University of Leicester and the chief investigator for the PHOSP-COVID study, said:

“While the profile of patients being admitted to hospital with COVID-19 is disproportionately male and from an ethnic minority background, our study finds that those who have the most severe prolonged symptoms tend to be white women aged approximately 40 to 60 who have at least two long term health conditions, such as asthma or diabetes.”

The researchers were able to the classify types of recovery into four different groups or ‘clusters’ based on the participants’ mental and physical health impairments.

One cluster group in particular showed impaired cognitive function, or what has colloquially been called ‘brain fog’. Patients in this group tended to be older and male. Cognitive impairment was striking even when taking education levels into account, suggesting a different underlying mechanism compared to other symptoms.

Dr Rachael Evans, an associate professor at the University of Leicester and respiratory consultant at Leicester’s Hospitals, said:

“Our results show a large burden of symptoms, mental and physical health problems and evidence of organ damage five months after discharge with COVID-19. It is also clear that those who required mechanical ventilation and were admitted to intensive care take longer to recover. However, much of the wide variety of persistent problems was not explained by the severity of the acute illness - the latter largely driven by acute lung injury - indicating other, possibly more systemic, underlying mechanisms"

The pre-print, title, which is yet to be peer-reviewed, is now available to view on Med Archives.


Thank you to all of our research teams who are making such a different to people’s lives, and also to Southmead Hospital Charity which is raising much-needed funds for COVID-19 research.

Take Part in Research
Patient & Doctor viewing an x-ray

Become one of the thousands of people taking part in research every day within the NHS.

Contact Research

Research & Development
North Bristol NHS Trust
Level 3, Learning & Research building
Southmead Hospital
Westbury-on-Trym
Bristol, BS10 5NB

Telephone: 0117 4149330
Email: research@nbt.nhs.uk
R&I PHOSP COVID.jpg

Results: Information about being a carrier

Regular Off Off

Information about being a carrier

Some women receive a test result that requires further discussion and / or follow up. How this happens will depend upon the type of test that that requires following up. In some cases you will be contacted by your Community Midwife, who will explain the test result to you and tell you what might happen next.

Alternatively you may be contacted by a Specialist Screening Midwife or Fetal Medicine Midwife who will explain things to you and talk to you about the test result and what might happen next. Some women are referred to other specialist services and your Community Midwife or Specialist Midwife will arrange this.

Scan findings are discussed at the time of the scan. If there are any concerns, women will be referred to a fetal Medicine Consultant for further scans and discussion of the findings. (See Fetal Medicine page).

The following link to the government website will direct you to information leaflets relating to a number of conditions. Scroll down the page to find additional information on sickle cell, thalassaemia and other haemoglobin variants; infectious diseases; 11 physical conditions relating to the 20 week scan; diagnostic tests. www.gov.uk

Mechanical clot retrieval for ischaemic stroke

Regular Off Off

Information for friends and relatives about mechanical clot retrieval for ischaemic stroke at North Bristol NHS Trust. 

What has happened?

Your friend or relative has had an ischaemic stroke and needs an emergency procedure. 

Strokes happen when an artery (blood vessel) is blocked by a clot, cutting off blood flow to part of the brain. Without a blood supply, brain cells can be damaged or destroyed because they may not receive enough oxygen. 

Symptoms may have included numbness or weakness on one side of the body, problems with balance, speech, vision, and/ or swallowing.

What is thrombolysis?

Thrombolysis is a drug treatment which is given within 4 hours of an ischaemic stroke to dissolve the blood clot. 

It is a treatment that is not suitable for everyone and is less effective than mechanical thrombectomy when the clot is large. Certain medications or medical conditions may mean that thrombolysis is not the suitable for all patients.

What is mechanical clot retrieval?

  • Mechanical clot retrieval aims to remove the blood clot from the affected artery in the brain, restoring blood flow and minimising brain tissue damage.
  • The procedure is often done using general anaesthesia (patient will be asleep).
  • A thin tube called a catheter is inserted into an artery, usually in the groin, and moved towards the site of the clot. The clot retrieval device is inserted through the catheter.
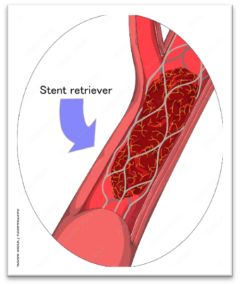
  • Different devices and methods are used to remove blood clots. The most commonly used device is called a stent retriever, which traps and removes the clot.
  • The aim is to remove the clot as soon as possible, within a few hours of the stroke to restore blood flow to the affected area of the brain.

The procedure is only suitable for some patients, a healthcare team experienced in managing acute ischaemic stroke will decide if you are suitable for this procedure. The following will factors will be taken into consideration:

  • The vessel the blood clot is in.
  • The time the stroke happened.
  • Other medical conditions.
  • The patients ability to care for themselves.

Stent retrieval of a clot 

Diagram or artery with stent retriever around blood clot

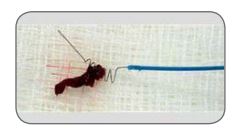
Clot that has been removed

Picture of a clot that has been removed

Who will do the procedure?

An experienced Consultant Neuro Interventional Radiologist and their team will perform the procedure in the radiology department.

The Interventional Radiology nurses and the Stroke Nurse Practitioner will keep in close contact and keep you updated after the procedure.

External transfers to Southmead Hospital

Patients who have been transferred to Southmead Hospital will be reassessed when they arrive, and they may also need further CT scans.

Please be aware that patients may no longer be suitable for treatment once they arrive, if further damage to brain tissue has happened.

Occasionally after thrombolysis the clot may have dissolved, or moved to an artery further away that is not suitable for a thrombectomy. In this case the patient will be transferred back to their local hospital for ongoing care and investigations.

In some cases, patients may have had worsening of their stroke symptoms, and the area of damage (ischaemia) has become larger. In these cases, the procedure is unlikely to be helpful.

Patients may need to stay at Southmead for observation if they are unwell or may transfer directly back to their local stroke centre or hospital.

What are the benefits of mechanical clot retrieval?

The procedure has been shown to significantly improve chances of surviving and preserving quality of life, if done within the first twelve hours of symptoms starting. This will be alongside other specialist medical treatment and care.

The aim is to prevent stroke symptoms getting worse, but does not reverse the damage that has already occurred to the brain.

The procedure can be done up to 24 hours after a stroke, depending on the level of damage in the brain. Every patient is different, and some patients may experience irreversible damage to the brain quicker than others.

What are the risks of mechanical clot retrieval?

The brain is fragile following a stroke, and there is risk of causing bleeding by puncturing a vessel during the procedure. This can cause severe disability or death.

There is also a risk of groin site bleeding, abdominal internal bleeding, or disrupted blood supply to the lower limbs which may need further surgery.

There is a small risk of infection at the groin site.

What happens after the procedure?

  • After the procedure, patients go to the recovery unit where staff closely monitor blood pressure and groin site.
  • Occasionally patients may need to go to the intensive care unit if specialist blood pressure treatment is required for a short time.
  • Otherwise, patients will go to the hyperacute stroke ward (Ward 34B).
  • Patients will have close monitoring and observations, which will include heart monitoring, frequent measurements of blood pressure, heart rate, and oxygen saturation levels.
  • Staff will test the strength in arms/legs, speech, and level of consciousness.
  • Any signs of neurological deterioration will be detected quickly and patient will have further CT scans as necessary.
  • Patients will usually stay in this area for 48-72 hours before being moved to the acute stroke unit area of the ward.

What happens after the procedure?

  • If your friend or relative came from another hospital then they will stay with us until they are stable to return to their local hospital. This is normally 24-48 hours.
  • It will depend on the type and severity of your stroke.
  • It will depend how well they are recovering and whether they need rehabilitation.

Strokes affect everyone differently and recovery from depends on many factors:

  • Where the stroke occurred in the brain.
  • The severity of the stroke.
  • The age of the patient and their medical history.

If you have any questions about the procedure or care following the procedure, do not hesitate to speak to any of our stroke team. This leaflet is only a starting point for discussion and our doctors and nurses can answer any of your queries during your friend or relatives stay.

You can contact the Hyperacute Stroke Unit on: 0117 414 3600.

References and further information

The Stroke Association

0303 303 3100

Stroke Association / Finding strength through support

Stroke association information about thrombectomy

What is Thrombectomy? | Stroke Association

Bristol Area Stroke Foundation

0117 964 7657

Bristol After Stroke | Home


© North Bristol NHS Trust. This edition published July 2024. Review due July 2027. NBT003017.

It's okay to ask

Illustration of 3 clinicians wearing blue scrubs with stethoscopes around necks

Find out about shared decision making at NBT. 

COVID-19 CCP/ISARIC Study

Regular Off Off

The purpose of ISARIC CCP-UK (International Severe Acute Respiratory and emerging Infection Consortium Clinical Characterisation Protocol United Kingdom) is to prevent illness and deaths from infectious disease outbreaks.

It is a global federation of clinical research networks, providing a proficient, co-ordinated, and agile research response to outbreak-prone infectious diseases. The Clinical Characterisation protocol (CCP) is designed for any severe or potentially severe acute infection of public health interest and feeds into the data collated by ISARIC.

The protocol allows data and biological samples to be collected rapidly in a globally-harmonised manner. It has been previously initiated in response to other acute infections, including MERS-CoV and Ebolavirus, and has now been initiated in 2020 for COVID-19.

All patients admitted to the Trust with a diagnosis of COVID-19 are enrolled with data collected on demographics, co-morbidities, signs, symptoms, treatments and outcomes.

A subset of patients will be consented into sub studies which will include additional biological sampling. This data can be combined globally to provide information on those most at risk, common signs and symptoms and also help establish treatments.

Take Part in Research

Patient & Doctor viewing an x-ray

Become one of the thousands of people taking part in research every day within the NHS.

Contact Research

Research & Development
North Bristol NHS Trust
Level 3, Learning & Research building
Southmead Hospital
Westbury-on-Trym
Bristol, BS10 5NB

Telephone: 0117 4149330
Email: research@nbt.nhs.uk
R&I CCP-ISARIC.jpg

COVID-19 GenOMICC Study

Regular Off Off

The GenOMICC (Genetics of Susceptibility and Mortality in Critical Care) study seeks to identify the specific genes that cause some people to be susceptible to specific infections and consequences of severe injury.

When a patient is already sick, different genetic factors determine how likely they are to survive, and our genes are what determine how susceptible we are to life-threatening infection.

Susceptibility to COVID-19 is almost certainly, in part, genetic. By identifying these genes, we should be able to determine the best use of existing treatments, and design new treatments to help people survive critical illness. This will be achieved by comparing DNA and cells from carefully selected patients with samples from healthy people.

GenOMICC was designed for this crisis. Since 2016, the open, global GenOMICC collaboration has been recruiting patients with emerging infections, including COVID-19. All patients with confirmed COVID-19 in critical care are eligible for this study.

GenOMICC is prioritised as an NIHR Urgent Public Health Study in the UK.

Take Part in Research

Patient & Doctor viewing an x-ray

Become one of the thousands of people taking part in research every day within the NHS.

Contact Research

Research & Development
North Bristol NHS Trust
Level 3, Learning & Research building
Southmead Hospital
Westbury-on-Trym
Bristol, BS10 5NB

Telephone: 0117 4149330
Email: research@nbt.nhs.uk

R&I GENOMICC.jpg

North Bristol Trust: Thrombectomy Referral Criteria – External Hospitals

Regular Off Off

North Bristol Trust: Thrombectomy Referral Criteria – External Hospitals

Thrombectomy service for patients from the Severn region, England operate 24/7.

Referrals from outside Severn and Wales should be discussed with your nearest thrombectomy centre. If the referral time falls outside operating hours for your nearest thrombectomy centre then please discuss with us via referapatient. 

Referrals should be made via Homepage (referapatient.org) to North Bristol Trust in the first instance

   (Search ‘Mechanical Thrombectomy’ and ‘Southmead Hospital’)

If no response is received in 10 minutes, please phone the thrombectomy phone directly

 07784 359723

In case of difficulties, alternative contacts are stroke registrar bleep 1490, or ANPs 0117 9549092.

Before referral, the following should have been carried out:

  • Upload of all new brain imaging to cloud portal (Biotronics 3Dnet).
  • Input all referral information via: Homepage (referapatient.org)
  • Where intravenous thrombolysis is indicated this should not be delayed.

Referrals should fulfil all of the following criteria:

Clinical

  • NIHSS >= 6 or disabling/fluctuating deficit
  • Independent before the index stroke (modified Rankin Scale 0-2).
  • Fit for emergency transfer. If concerns exist regarding patients being safe for inter-hospital transfer seek advice from local anaesthetic / critical care team
  • Sufficiently well to benefit from treatment. This includes co-morbidities and frailty; while age influences fitness for treatment age does not by itself limit capacity to benefit.

Radiological

  • All patients should undergo a NCCT and CTA with coverage from aortic arch to the vertex*
    • This should be uploaded to Biotronics 3DNet routinely,
    • This should have a local diagnosis of an LVO (carotid-T, M1, proximal M2 or tandem occlusions) via a consultant radiologist or automated post processing tool such as Rapid or Brainomix.

*Multi or dual phase CT angiography is preferred.

  • For patients arriving at Southmead within 6 hours:
    • NCCT and CT angiography is required.


  • For patients arriving at Southmead within 12 hours:
    • NCCT and CT angiography is required. 
    • Minimal early ischaemic change required (defined as NCCT ASPECTS >= 3 if perfusion imaging is not available locally).
    • Additional CT perfusion with automated post processing is preferable.


  • For patients arriving at Southmead between 12 and 24 hours:
    • NCCT, CT angiography and CT perfusion is required. 

NOTE:   If a patient does not fulfil the above criteria but it is felt that they would benefit from treatment, for example young patient with large ischaemic core, basilar occlusion, referrals will still be considered

Please ensure a ReSPECT  form has been completed prior to transfer


Elective Patients Awaiting Surgery

Submitted by Jessica Knott on

Status message

Sorry… This form is closed to new submissions.

On Regular

Thank you for responding to our letter in relation to the review of all patients on our waiting list awaiting surgery. 

We would like to understand your current position and future treatment wishes and therefore, request that you complete the form below.

Eating well with diabetes whilst in hospital

Regular Off Off

What is diabetes?

Diabetes means the body can no longer control the level of glucose (sugar) in the blood. Our bodies make insulin (a hormone) which allows glucose in the blood to be used by the body for energy. In diabetes:

  • The body doesn’t produce any insulin, or        
  • The body doesn’t produce enough insulin, or            
  • The body cannot use insulin efficiently (most common)

The body particularly struggles to use insulin when you are unwell. 

Aims of this page

When a person with diabetes is unwell, glucose levels often rise as a result of the illness.  High glucose levels can lead to further problems and a longer stay in hospital.  For this reason, your diabetes medication may need to be adjusted. You will have help to do this in hospital. It is also important that you continue to follow a healthy balanced diet.

The information on this page is designed to help you to:

  • Understand the importance of a healthy balanced diet in diabetes
  • Understand North Bristol NHS Trust’s menus
  • Understand the importance of making an individualised choice at mealtimes

Does it matter what I eat?

Yes. What you eat affects the levels of glucose and fat in your blood, your blood pressure and your weight. It is therefore important to follow a healthy, balanced diet. The below recommendations are the same as for the general population. 

Healthy eating involves:

  • If you are overweight, try to lose some weight (when you are well).
  • Eat at regular intervals during the day i.e. breakfast, midday and evening meal. Don’t miss meals.
  • Include starchy food (carbohydrate) at each meal (approximately one quarter to one third of the plate). Aim to have about the same amount of starchy food each day. Go for wholegrain, high fibre options where possible.
  • Have two or three portions of vegetables each day.
  • Have two or three portions of fruit spread throughout the day.
  • Limit foods with a high fat content.
  • Cut down on sugar, sugary foods and sugary drinks (this includes smoothies and fruit juice).
  • Drink alcohol in moderation.
  • Cut down on salt.
  • Special diabetic foods are not necessary.

Further information is available on healthy eating with diabetes.

Is there a diabetes specific menu in hospital?

No. Healthy eating recommendations are the same as for the general population. There is no need for a specific ‘diabetes menu’ or meal options to be coded as ‘suitable for individuals with diabetes’. The main menu at Southmead Hospital offers a variety of options that allows a person to eat a balanced diet. 

Please note some main courses from the menu already contain a portion of starchy carbohydrates. For example, cheese and potato pie already has a portion of carbohydrate in it in the form of potato. In this instance, you may wish to choose two vegetable side dishes rather than a further potato, pasta or rice accompaniment.

Menu options which contain high amounts of sugar should be limited

Some options on the menu are higher in calories and sugar. Examples include: fruit crumbles, sticky toffee pudding, bread pudding or parkin cake, sponge puddings, rice pudding, chocolate crunch etc

Due to their high sugar content, these options may significantly increase blood glucose levels. Intake of these options should be limited. Small portions of these can be enjoyed occasionally.

Lower sugar and calorie alternatives include:

  • Fruit in natural juices
  • A portion of stewed fruit
  • A small pot of yoghurt

Some patients in hospital may be identified as being at ‘higher nutritional risk’:

  • If the patient is underweight.
  • If the patient has recently lost weight.
  • If the patient has a poor appetite and intake (how much food they eat).

These patients are encouraged to increase the amount of food they eat. They will benefit from having some of the higher calorie and sugar options, as noted above. This is not the case for everyone in hospital and meals should be chosen on an individual basis. Please ask the ward staff for support if you are unsure.

Hospital meal times

Meal times in hospital may be at different times to at home. Depending on the type of medication or insulin you take to manage your diabetes, the difference in meal times could increase your risk of having a ‘hypo’ (blood glucose less than 4mmol/L). 

If you take rapid-acting insulin (NovoRapid™, Humalog™, Apidra™ or Fiasp™) with meals, it is advised that you wait until your meal has been served to you before injecting your insulin. This reduces your risk of having a hypo if the meal is delayed, is different to what you ordered, or you don’t expect to eat the full portion.

Snacks such as cereal, toast, sweet biscuits and milky drinks are routinely available on the ward. Please ask a member of ward staff if you require a snack to prevent a hypo if your meal is delayed, at a different time to home, or, if you have been advised to have a snack before bed.

References

Healthy Eating with Diabetes

The Nutrition and Hydration Digest 3rd Edition - BDA (last updated June 2023)

Evidence-based nutrition guidelines for the prevention and management of diabetes | Diabetes UK (last updated March 2018) 

Type 1 diabetes in adults: diagnosis and management (last updated August 2022)

Type 2 diabetes in adults: management (last updated February 2026)

How to contact us

See your appointment letter for the number to phone with any queries you may have.

Date published: 18 September 2026 Review due: 30 September 2029 PI number: BFT003110
 

Carers and Young Carers Charter

Regular Off Off

Promoting a culture of supporting and working in partnership with carers within our hospitals

North Bristol NHS Trust (NBT) and University Hospitals Bristol and Weston NHS Foundation Trust (UHBW) value the vital work done by those with unpaid caring responsibilities (referred to as ‘carers’ within this charter) and are committed to working together with them as expert partners in care.

A carer is someone who provides care for someone else who, due to illness, mental health problems, substance misuse, physical and learning disability, old age or frailty, is unable to care for themselves without their support. This charter includes young carers and parent carers.

Carers as equal partners

We will ensure that the role you have, as a carer, is valued by all staff and will make sure that we respect, listen to and understand carers and what they do. We will identify carers as early as possible.

Supporting carers

We will inform you as a carer of your right to an assessment under the Care Act 2014 and the Children & Families Act 2014, providing information about the range of support and advice services available to you as a carer. We recognise the importance of your needs being met and will support you to have breaks away from the ward when you need them.

Young carers

We will ensure that we involve young carers and will work to support you and recognise the valuable role you play in the health of our patients.

Sharing information

With the relevant consent obtained, we will provide information that is timely, appropriate and accessible. We will involve you in decision making, with the patient wherever possible, whilst respecting the need for confidentiality.

Having a voice

We will ensure that you have an easily accessible means of giving feedback, that this is responded to and that you are involved in the planning and development of our services.

Discharge planning

We will begin discharge planning as soon after admission as possible. We will help you understand the processes, including you in all discussions, respecting your detailed knowledge of what happens outside the hospital. With the relevant consent obtained, we will include you in all discussions on all aspects of care and medication. 

To contact us

Please email: carerliaison@carersbsg.org.uk

Ring and ask for the Carers Liaison Support Worker for North Bristol Trust:

CarersLine: 0117 939 2562 option 3 

Young Carers: 0117 958 9980

Ask the ward to refer you.

How to inject enoxaparin at home

Regular Off Off

This information is for patients who have been directed to this page as you are starting, or already taking, a medicine, known as enoxaparin. It is most likely that the enoxaparin brand you will be using is called Inhixa®. Enoxaparin is part of a group of medicines called anticoagulants. An anticoagulant medicine prevents blood clots forming in your blood vessels by making your blood take longer to clot.

Enoxaparin contains a product derived from pigs. If you have any ethical objections to the use of animal products please discuss this with a healthcare professional before using enoxaparin.

Enoxaparin reduces blood clot risk

A blood clot can develop in the large veins of the body, usually in the legs. This is called a deep vein thrombosis (DVT). 

Sometimes, a blood clot can break free and travel through your blood vessels. If a clot lodges in the blood vessels of your lungs it is called a pulmonary embolism (PE). A PE can cause chest pain and difficulty in breathing and, if severe, can cause death. Rarely, a clot may move to the brain and cause a stroke. 

After surgery there is an increased risk of blood clots forming. Evidence shows that following some types of surgery, an extended period of treatment with enoxaparin reduces this risk. You will usually need to inject enoxaparin for between 10 and 28 days after your surgery.

Why do I need enoxaparin?

There are lots of reasons why you may be at higher risk of blood clots. Here are some of the most common ones:

  • Age over 40, as the risk increases with age.
  • Taking any kind of oral contraceptive pill (OCP).
  • Taking hormone replacement therapy (HRT).
  • Some heart problems.
  • Severe breathing difficulties.
  • Varicose veins.
  • Obesity .
  • If you have had a DVT before.
  • If you have a family history of DVT.
  • If you have previously suffered a stroke.
  • The type of surgery, such as knee or hip replacement or abdominal surgery.

How can I tell if I have a DVT or PE?

Early signs of a deep vein thrombosis (DVT)

When you have a deep vein thrombosis, you may notice any of the following signs in one or both legs:

  • Pain or tenderness in the calf or thigh.
  • Swelling, redness, or skin colour changes.
  • Warmth in your calf or leg.


Early signs of a pulmonary embolism (PE)

You are much more likely to notice something is wrong if you have a blood clot in your lungs (PE). You may notice one or more of these signs:

  • Chest pain.
  • Shortness of breath.
  • Coughing or coughing up blood.
  • Racing heartbeat or fast pulse.
  • Rapid breathing.
  • Tiredness.
  • Feeling feverish (temperature above 38.3°C).

If you think you may have a DVT or PE, contact your doctor immediately for advice.

How should I inject enoxaparin?

You need to inject Inhixa® under the skin (a ‘subcutaneous injection’). You should have the injection at the same time every day. 

A healthcare professional will have shown you how to inject yourself using the Inhixa® syringe. They should also tell you how long the treatment will be for. It is important that you know the correct technique before you try to inject yourself. If you are unsure, you should ask a healthcare professional for advice.

Step-by-step instructions for injecting Inhixa®

Note: There are different brands of enoxaparin, the below instructions are for the Inhixa® brand. If these instructions are different from those your nurse or doctor has given you, please follow their advice or the instructions included with your product.

  1. Wash your hands with soap and water. Dry them thoroughly.
  2. Sit or lie in a comfortable position so that you can see the part of your stomach where you are going to inject. It may help if you can prop yourself up with cushions or pillows, either on a bed or in an armchair. Make sure that your safety bin (sometimes known as a ‘sharps bin’) is within reach.
  3. Choose an area on either the left or the right side of your stomach. This should be at least 5cm away from your belly button and out towards your sides.
    Remember: Do not inject yourself within 5cm of your belly button or around existing scars or bruises. Change the place where you inject each day between the left and right sides of your stomach, depending on the area you last injected.
  4. Remove the plastic blister containing the pre-filled syringe from the box. Open the blister and remove the pre-filled syringe
  5. Carefully remove the protective cap from the end of the syringe, taking care not to bend the needle. Throw the needle cap away in your safety bin; you will not need it again. The syringe is pre-filled and ready to use.
  6. Do not press on the plunger before injecting yourself. Once you have removed the cap, do not allow the needle to touch anything. This is to make sure the needle stays clean (sterile).
    Make sure you hold the skin fold throughout the injection.
  7. Hold the syringe in the hand you write with (like a pencil). With your other hand, gently pinch the area of your abdomen between your forefinger and thumb to make a fold in the skin.
  8. . Press down on the plunger with your thumb. This will inject the medicine into the fatty tissue of the abdomen. Make sure you hold the skin fold throughout the injection.
  9. Remove the needle by pulling it straight out. Do not release the pressure on the plunger.
    To avoid bruising, do not rub the injection site after you have injected yourself
  10. Push hard on the plunger. The needle guard, which is in the form of a plastic cylinder, will be activated automatically and it will completely cover the needle.
  11. Drop the used syringe into the sharps container. Close the container lid tightly and place the container out of reach of children. When the container is full, dispose of it as instructed. Do not put it in the household rubbish. If you require an additional bin, please contact your GP surgery

Things to look out for

As with all medicines, enoxaparin can have side effects in some people. Please see the patient information leaflet supplied with your injections for more advice on possible side effects. 

The most common effect is that you may be more susceptible to bruising and bleeding than usual. You may also notice mild irritation or other reactions of the skin on your stomach where you have been injecting. These might include redness, pain, small hard bumps (known as nodules) or bleeding into the skin (sometimes called a haematoma).

These effects may be caused by your injection and may occur some time after an injection. There may also be a sign of infection; if you notice redness, puffiness, warmth, skin discolouration or oozing of the skin near a previous injection, you should contact your nurse or doctor straight away. 

If you notice any of the following effects, please contact your nurse or doctor at once:

  • Bleeding from your surgical wound.
  • Any other bleeding – for example, from the skin where you have injected, nosebleeds, blood in your urine (pink or dark brown), blood in your stools (bowel movement), black tarry stools, or if you cough up blood.
  • Unusual bruising not caused by a blow or any other obvious reason.

You should also tell your nurse or doctor if: 

  • You have a serious fall or head injury.
  • You notice any other unusual symptoms.

Heparin-induced thrombocytopenia (HIT)

Another issue to look out for is heparin-induced thrombocytopenia (HIT). Enoxaparin contains heparin, which in rare cases, can cause a fall in platelets. This typically occurs 5 to 10 days after starting treatment with enoxaparin.

Platelets are a component of blood which are involved in blood clotting to stop bleeding. When there are too few in the blood, this is termed thrombocytopenia and this results in an increased risk of bleeding.

Signs of heparin-induced thrombocytopenia include:

  • Weakness or numbness in the arms or legs.
  • Pain, tenderness, redness, or swelling of the arms or legs.
  • Flushing, black, reddish, or bluish discoloration of the skin, or a rash or skin sores in the area where the enoxaparin injection was given.
  • Chest pain or tightness, or fast or troubled breathing.
  • Fever, chills or sweating.
  • Slurred speech, increased sleepiness, or problems seeing, talking, thinking or remembering.

If you think you may be affected by HIT then contact your doctor immediately for advice. A blood test can then be performed to check if this is occurring.

Dos

  • Do make sure you keep holding the fold of skin on your abdomen until you have completely finished your injection. This will help ensure that the medicine goes into the fatty tissue rather than muscle, which could bruise.
  • Do alternate the side on which you inject – right one day, left the next.
  • Do make sure you put your used syringes into the safety bin each time you inject – never leave a used syringe lying around.
  • Do follow the advice of your nurse or doctor when using your enoxaparin injections.
  • Do try and carry out your injection at the same time every day. Do look for unusual signs of bleeding, and get assistance if these occur.

Don'ts

  • Don’t put the syringe down anywhere or touch the needle with anything before you inject – this will help reduce the risk of infection.
  • Don’t twist off the needle cap, as this could bend the needle.
  • Don’t inject into bruised or scarred skin or anywhere that might be rubbed by clothing.
  • Don’t rub the skin after you have injected, as this can cause bruising.
  • Don’t let anyone else use your enoxaparin syringes.
  • Don’t put enoxaparin in the fridge or freezer – keep it at room temperature.
  • Don’t take any of the following medicines while you are using enoxaparin without discussing it with your nurse or a doctor first. (Note that these medications can be used after surgery so check if this is okay with your doctor or nurse): 
    aspirin, or anything containing aspirin, pain relievers known as non-steroidal anti-inflammatory drugs (NSAIDS, such as ibuprofen).
  • Don’t use enoxaparin if you are allergic to enoxaparin or heparin.

Your questions answered

After discharge from hospital who can I contact for help or advice?

If you have any concerns or worries you should contact the ward you were discharged from and ask to speak to the nurse in charge. You should be given a contact number when you are discharged from hospital. Alternatively, contact the hospital switchboard on 0117 950 5050 who will be able to put you through to the ward.

The patient information leaflet that came with enoxaparin advises against using a particular medicine that I am taking. Is this okay?

If you have not already been advised by your nurse or doctor that this is okay, then you should contact your nurse or doctor for advice.

Can I inject anywhere other than my stomach?

You should ask your nurse or doctor for advice.

Where should I keep the enoxaparin syringes?

Unused syringes should be kept in a safe place out of reach of children. Keep them at room temperature, in the box provided and away from light and moisture.

What should I do if there is an air bubble in the syringe?

The syringe normally contains an air bubble. You do not need to do anything to remove the air bubble before you inject.

What should I do if I have injected too much enoxaparin?

You should contact your nurse or doctor for advice.

What should I do if I miss an enoxaparin injection?

You should contact your nurse or doctor for advice.

How can I find out more about enoxaparin?

You can read the patient information leaflet in the enoxaparin box.

What should I do with my used syringes?

Put used syringes (with the needle point facing down) into the safety or sharps collection bin you have been given. Always keep this out of reach of children. Never throw a safety bin away with your other household waste.

Collection of your used safety bin can normally be arranged with your local council. This depends on your local council:

For Bristol City Council 

Email: waste.services@bristol.gov.uk 

Phone: 0117 922 2100

For South Gloucestershire

You can complete an online form to request a sharps collection: Dispose of clinical and medical waste | BETA - South Gloucestershire Council (southglos.gov.uk)

Phone: 01454 868 000

For Bath and North East Somerset Council 

You can complete an online form to request a sharps collection: Clinical or sharps waste | Bath and North East Somerset Council (bathnes.gov.uk)

Phone: 01225 394041

For North Somerset

You’ll need to contact your doctor to ask for a sharps collection.

Email: clinicalwaste@n-somerset.gov.uk 

If you live outside these council areas please contact your GP practice or local community pharmacy for advice on clinical waste collection.

© North Bristol NHS Trust. This edition published January 2024. Review due January 2027. NBT002719